



A 70-year-old male patient with no relevant personal history was found at home with decreased level of consciousness and right hemiplegia. Brain CT scan revealed thrombotic occlusion in M1 of the left middle cerebral artery. Transesophageal echo was performed to investigate a possible cardiac source of the thrombus.
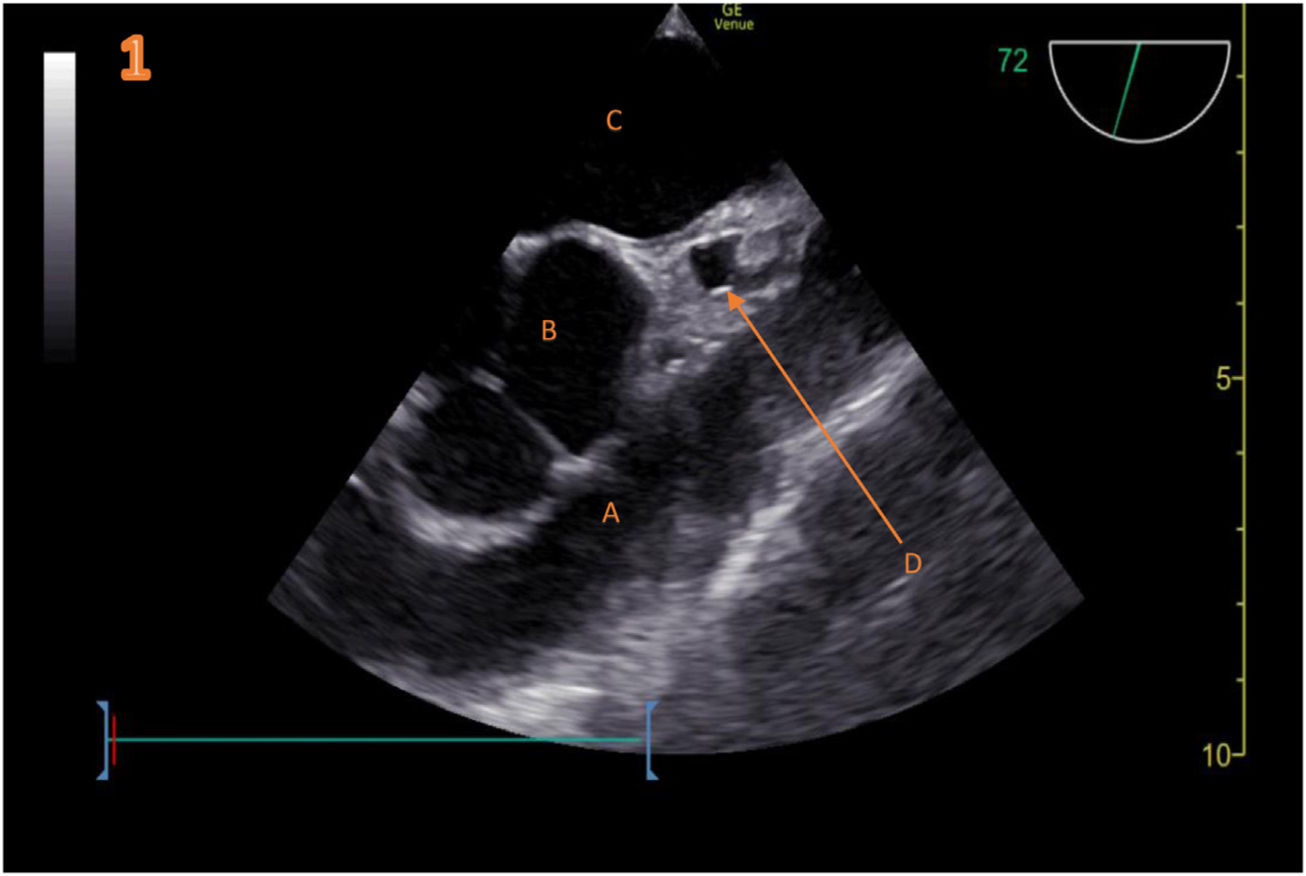
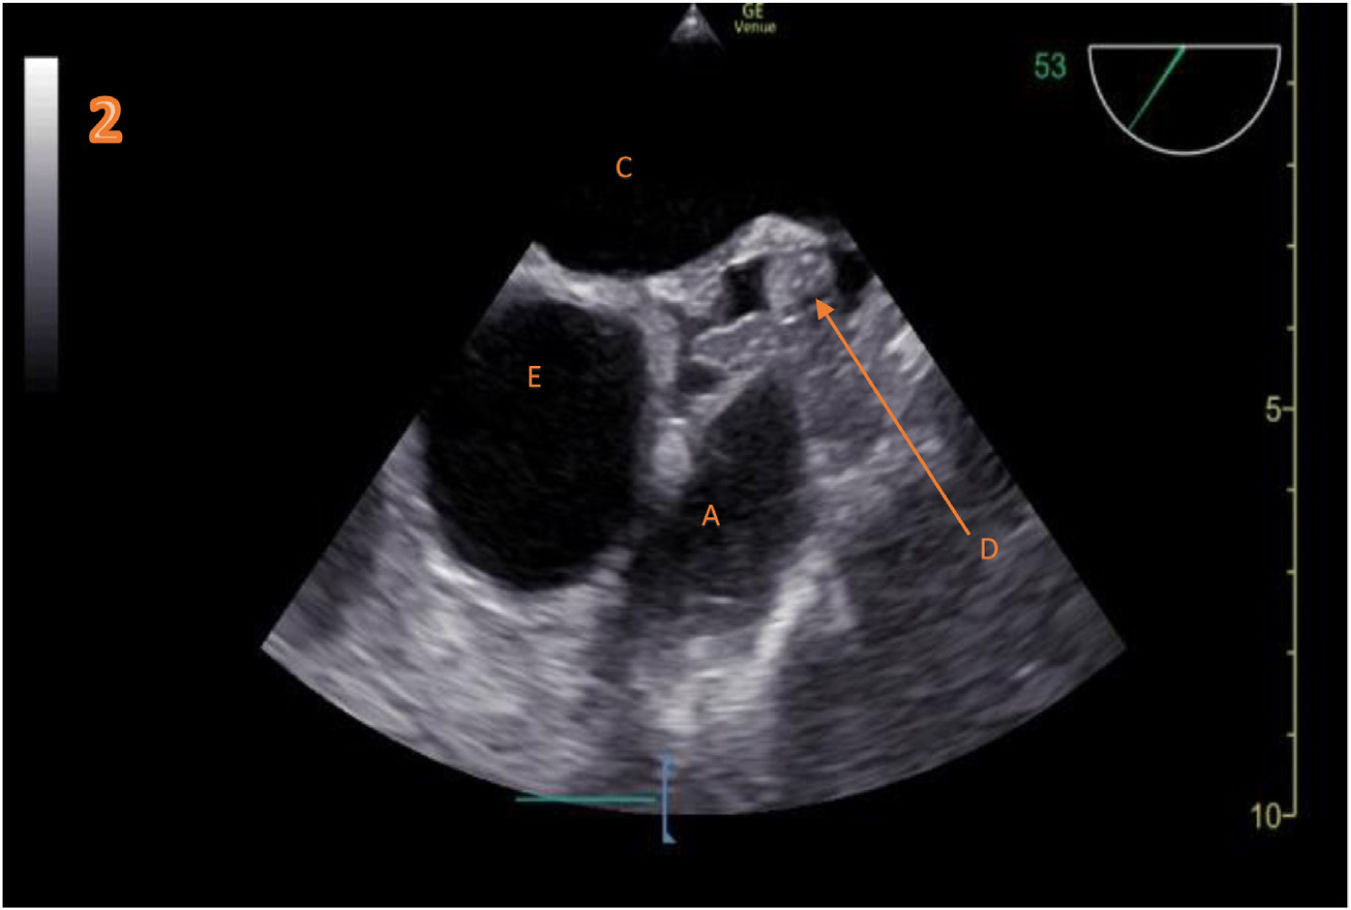
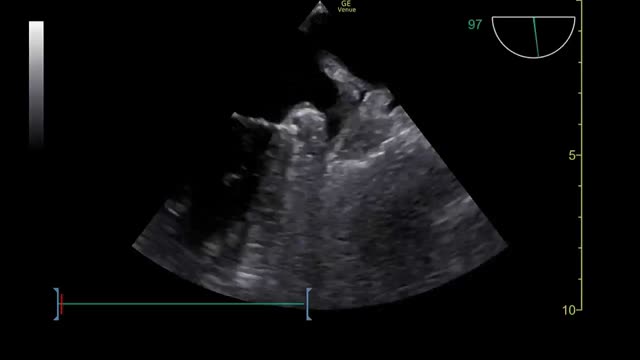
The left atrial appendage (LAA) and the transverse pericardial sinus are anatomically related structures. A small amount of fluid within transverse sinus is common, however, the presence of a pericardial fat pad inside may mimic an intra-LAA thrombus on echocardiography (Fig. 1 Mid-esophageal aortic valve short axis view, Fig. 2 Image obtained after a slight retraction of the probe. A: right ventricular outflow tract. B: aortic valve. C: left atrium. D: transverse pericardial sinus fluid-filled with pericardial fat inside. E: ascending aorta).


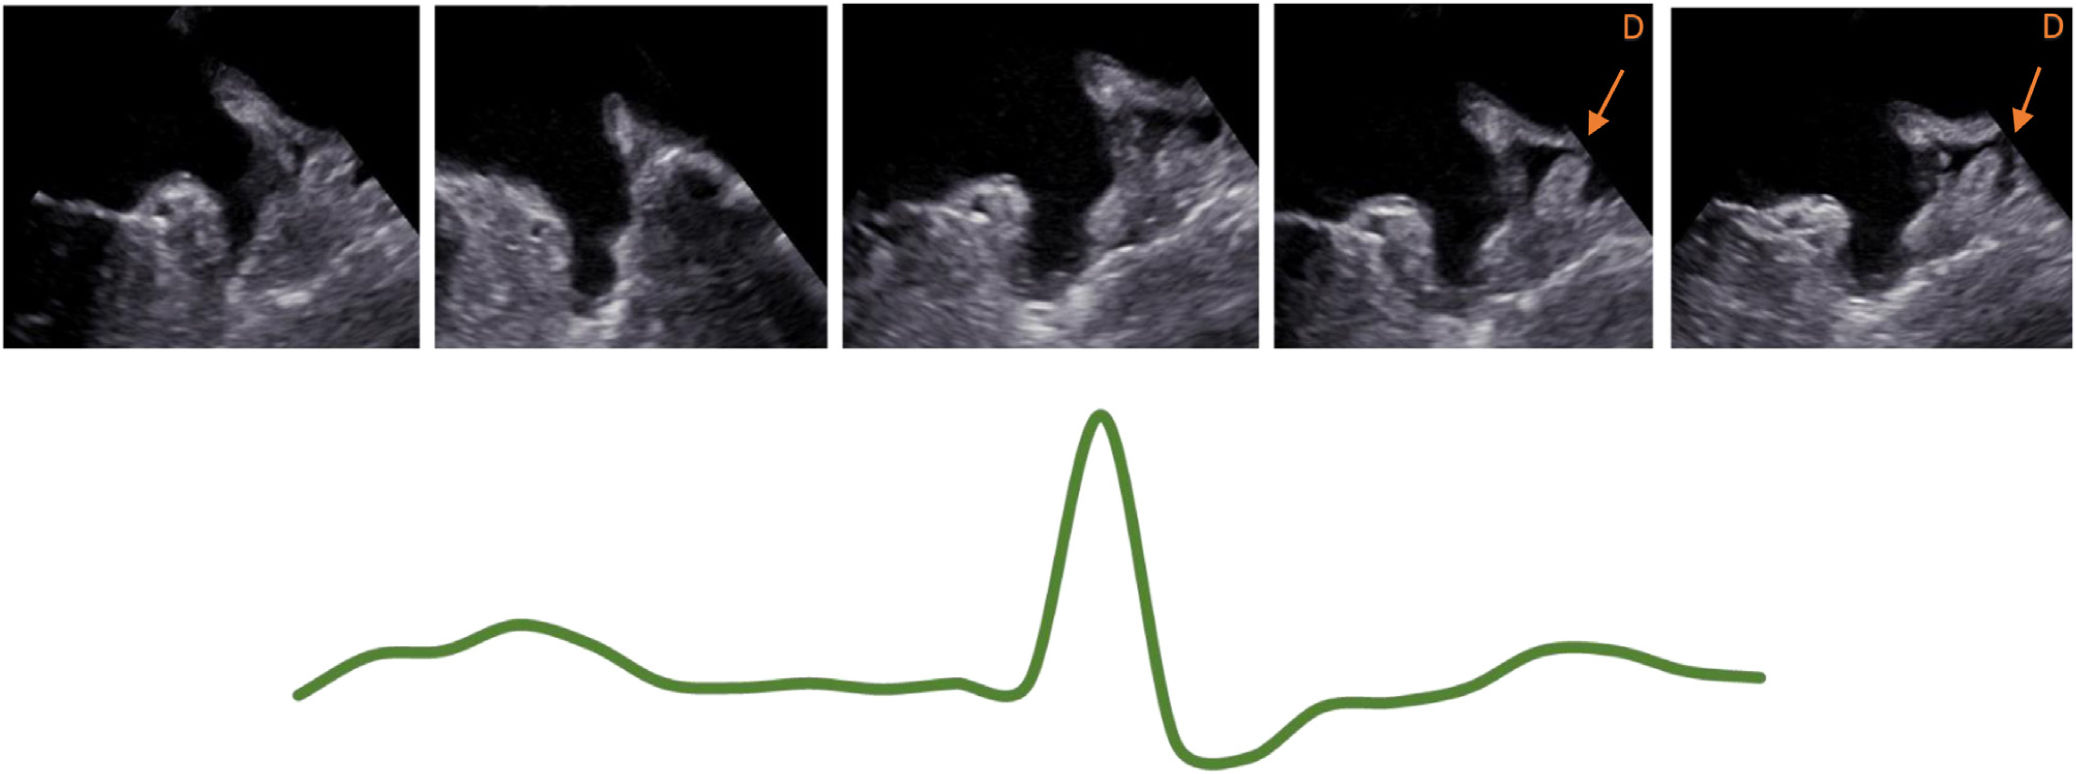
Fig. 3 (Mid-esophageal two-chamber view focused on left atrial appendage (LAA) view. D: transverse pericardial sinus fluid-filled with pericardial fat inside) shows changes in LAA during the cardiac cycle are observer. The LAA, with a “chicken wing” morphology, and the adjacent transverse pericardial sinus, are both visible. The appearance of pericardial fat pad within a fluid-filled transverse sinus may mimic a thrombus in the apex of LAA. In this case, correct identification of the pericardial recess is key to diagnosis.

Sometimes this structure can also be observed in chest CT scans and may be misinterpreted as adenopathy or mediastinal masses. In this case, ETE may be useful for diagnosis. Awareness of this anatomical relationship can prevent misdiagnosis and avoid initiation of inappropriate anticoagulation, with the risks that this entails.
Videos in supplementary material.
Informed consentThe patient consented to the use of their data for clinical research purposes.
Ethics declarationsThis publication complies with ethical recommendations related to the scientific publication process.
The authors declare to have no conflict of interest related to this work.



