





Trauma is the leading cause of death in children and adolescents. This article reviews recent advances in the management of severe pediatric trauma, emphasizing the importance of well-organized trauma systems, effective triage, and protocols specifically adapted to pediatric physiology. Current strategies for damage-control resuscitation are discussed, including the use of blood products, vasoactive support, and novel predictive indices for shock severity. In traumatic brain injury, the role of multimodal neuromonitoring and individualized management of intracranial and cerebral perfusion pressures is reviewed. The need to move beyond adult-centered approaches and tailor care to pediatric-specific characteristics is strongly emphasized. Finally, the main research priorities in pediatric trauma are outlined, which are essential for improving survival and functional recovery in this vulnerable population.
El trauma es la principal causa de muerte en niños y adolescentes. El presente artículo revisa los avances recientes en la atención al trauma pediátrico grave, destacando la importancia de sistemas de trauma bien organizados, triaje efectivo y protocolos específicos adaptados a la fisiología infantil. Se analizan las estrategias actuales de resucitación con control de daños, incluyendo el uso de hemoderivados, soporte vasoactivo y nuevos scores de predicción de shock. En el traumatismo craneoencefálico, se revisa el papel de la neuromonitorización multimodal así como la gestión individualizada de la presión intracraneal y la presión de perfusión cerebral. Se enfatiza la necesidad de adaptar los cuidados a las particularidades pediátricas, alejándose de modelos exclusivamente derivados de adultos. Finalmente, se presentan las principales líneas de investigación en trauma pediátrico, fundamentales para mejorar la supervivencia y la recuperación funcional de los pacientes.
External causes (non-natural or violent causes, including accidents, suicides, and assaults) are now the leading cause of death among 1- to 19-year-olds, accounting for 34% of all deaths in 2023.1 These injuries have physical, psychological, and emotional sequelae that affect the quality of life of the children and their families.2 Part of this mortality is potentially avoidable through rapid, standardized healthcare adapted to children’s anatomical and physiological particularities (Table 1).3 It is important to remember that children are not miniature adults. Their characteristics determine the types and severity of injuries they sustain and the therapeutic approaches required. Additionally, adolescents have unique characteristics in terms of injury mechanisms, such as traffic accidents or assaults, as well as anatomical differences, including a high frequency of injuries to the torso, pelvis, and extremities.4 This makes it necessary to be aware of certain lesions that are more typical of adult patients, such as cerebrovascular and pelvic injuries.5,6 Pediatric trauma care should be based on rigorous protocols and integrated into a trauma system that addresses all stages of care. The present review discusses the most current recommendations in light of the scientific evidence and the peculiarities of this patient population.
Physiological and anatomical characteristics of the child.
| Characteristic | Consequence |
|---|---|
| Increased vagal tone | → Tendency towards bradycardia at laryngoscopy |
| Compensation in event of bleeding | → Hypotension only in advanced stages |
| Lower functional residual capacity | → Early hypoxia |
| Increased oxygen demand | |
| Greater surface/weight ratio | → Increased heat loss |
| Smaller size | → More energy per unit surface area |
| Wide range of sizes and weights | → Drug according to ideal weight |
| → Devices according to size | |
| Helplessness and inability to communicate | → Non-accidental or inadvertent injuries |
| → Presence of parents | |
| → Tendency towards TBI and scalp bleeding | |
| Greater cephalic proportion | → Brain injuries caused by deceleration |
| Weakness of cervical structures | → SCIWORA and DAI lesions |
| Open fontanelles (<6−12 months) | → Increased tolerance of intracranial hypertension |
| Tongue-mouth disproportion | → Different axial alignment |
| Lymphoid tissue hypertrophy | → Preparation for intubation |
| More higher and anterior larynx | → Lesser field of view |
| Short, narrow and collapsible trachea | → Ease of selective intubation and inadvertent extubation |
| Elastic rib cage-ribs | → Internal injuries without fractures |
| More mobile mediastinum | → Propensity towards greater involvement in presence of pneumothorax or hemothorax |
| Smaller and more flexible ribs | → Increase in abdominal injuries |
| Pelvis with lesser capacity | |
| Less developed musculature | |
DAI: diffuse axonal injury; SCIWORA: spinal cord injury without radiological abnormality; TBI: traumatic brain injury.
Trauma systems (TS) are a multidisciplinary, transverse approach to trauma patient care. They include accident prevention, prehospital care, transfer to useful centers, and rehabilitation. Although the definitions vary, with regard to trauma, a useful center is understood to have the human, technical and structural resources necessary to provide comprehensive and continuous care for severely traumatized patients. Due to the specific needs of pediatric patients, a specialized system is needed that incorporates all healthcare providers who can attend to them. This system can be integrated into any TS and adjusted according to the epidemiology and available resources.7 This approach requires the integration of all hospital centers together with the emergency systems, through unified care protocols and referral criteria, as well as specialized training programs. When properly structured, a TS optimizes resources, correlates each patient’s needs with each center’s characteristics, and promotes equitable and efficient care.8
Categorization of the trauma patient. Severity scales in pediatricsThe categorization of trauma patients as a process of victim selection according to treatment needs and transfer priority can be carried out by means of severity indices. These indices are mostly designed to indicate referral to higher-level centers for the most severely ill patients. These indices should be simple, validated, and practical. Although they standardize prehospital assessment, they have limitations and should be combined with clinical judgment.9
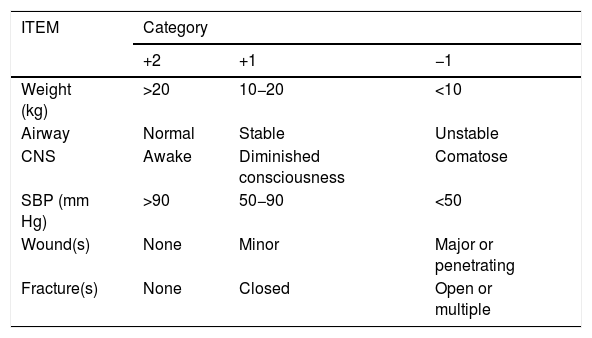
Pediatric trauma scoreThe pediatric trauma score (PTS) was designed as a triage tool to be used in prehospital care based on the anatomical and physiological nature of the injuries. It was created as a specifically pediatric index, and the score is linked to the patient's need for transfer to a trauma center (TC) (Table 2). The PTS is a simple and easy-to-apply scale that includes 6 components: 3 anatomical and 3 functional. The score ranges from -6 points (maximum severity) to +12 points (minimum severity).10
Pediatric trauma index.
| ITEM | Category | ||
|---|---|---|---|
| +2 | +1 | −1 | |
| Weight (kg) | >20 | 10−20 | <10 |
| Airway | Normal | Stable | Unstable |
| CNS | Awake | Diminished consciousness | Comatose |
| SBP (mm Hg) | >90 | 50−90 | <50 |
| Wound(s) | None | Minor | Major or penetrating |
| Fracture(s) | None | Closed | Open or multiple |
If score is ≤ 8 points: refer to trauma center.
CNS: central nervous system; SBP: systolic blood pressure.
More than three decades ago, the predictive validity of the PTS was assessed, presenting a sensitivity of 95.8% and a specificity of 98.6% for predicting mortality with a score ≤ 8. It is also associated with a high weight of evidence: WoE(+) = 18.3 and WoE(−) = −13.7.11 Thus, practically all patients with scores > 8 survive, and mortality progressively increases below this figure, indicating transfer to a TC. Its simplicity and validity have made it the most widely used tool in pediatrics. Recent studies have confirmed its high discriminatory power.12
Pediatric trauma codes. Activation and criteriaThe "trauma code" is a system designed to coordinate the care for severe trauma patients by integrating the different responsible parties through communication and specific protocols for triage, destination selection, transfer, and team activation. The TC’s main objective is to ensure that each trauma patient receives care at the most appropriate center. In this regard, the prehospital activation criteria, in addition to the severity indices, are useful for this purpose. When well-defined, they minimize both undertriage (serious patients referred to non-specialized centers, with a target rate of less than 5%) and overtriage (transfer of non-serious patients to higher-level centers, with a target of less than 35%).13 Periodically updated since 1976, prehospital triage guidelines have evolved to improve their applicability and decrease under- and overtriage rates. The latest 2021 update simplifies the activation criteria into two risk categories (Appendix B Table 1 of the Supplementary material) and includes the pediatric age group. This update is adaptable to the healthcare reality of the TS.14
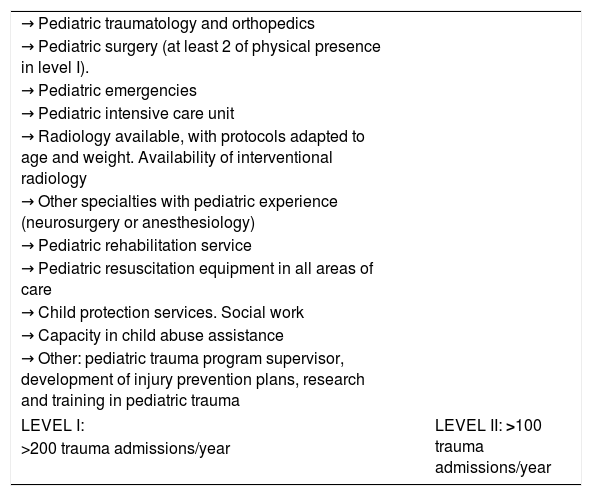
Pediatric trauma centersPediatric trauma centers (PTCs), created in the 1970s and 1980s, should provide leadership in pediatric trauma care in their territories through their own programs and research. They should also provide definitive care for the most severe cases and support to less specialized centers. The American College of Surgeons defines the resources needed by PTCs to maintain the competence of their teams (Table 3). Their number and location should be adapted to the population and needs of each territory. Several reviews have shown better outcomes for adults treated in TC. Although the evidence is not definitive, recommendations state that pediatric trauma care should also be provided in PTCs.8,15,16 A review published in 2023, including 34 studies and over 200,000 patients, reported a 40% reduction in mortality for patients under 16 years of age seen in PTCs, with a reduced use of computed tomography (CT) and less solid organ surgery.17 Other variables that could improve PTC care, such as the preservation of functionality,18 should also be considered.
Resources required for pediatric trauma center recognition as proposed by the American College of Surgeons Trauma Committee.8
| → Pediatric traumatology and orthopedics | |
| → Pediatric surgery (at least 2 of physical presence in level I). | |
| → Pediatric emergencies | |
| → Pediatric intensive care unit | |
| → Radiology available, with protocols adapted to age and weight. Availability of interventional radiology | |
| → Other specialties with pediatric experience (neurosurgery or anesthesiology) | |
| → Pediatric rehabilitation service | |
| → Pediatric resuscitation equipment in all areas of care | |
| → Child protection services. Social work | |
| → Capacity in child abuse assistance | |
| → Other: pediatric trauma program supervisor, development of injury prevention plans, research and training in pediatric trauma | |
| LEVEL I: | LEVEL II: >100 trauma admissions/year |
| >200 trauma admissions/year | |
The sequence of care is reviewed, and the main novelties are introduced. It should be noted that the current recommendations are mostly based on low-quality evidence or expert consensus.19
Primary assessmentThe aim is to identify and treat life-threatening conditions, rule out near-fatal risk injuries (NFRIs), and prevent secondary injuries.20
Pediatric assessment triangleWe will get a first impression by observing the following: 1) general appearance; 2) respiratory effort; and 3) peripheral perfusion, as well as obvious lesions and bleeding.21
ABCDE sequenceThe ABCDE sequence is recommended over C-ABCDE, unless massive hemorrhage is suspected.22
- A
Alertness-airway control-definitive cervical control
After determining whether the patient is conscious, presents diminished consciousness, or is comatose, the airway is evaluated. If endotracheal intubation is required, sedoanalgesia increases the risk of hemodynamic collapse and cardiorespiratory arrest (CRA). Administering volume and using ketamine as the sedoanalgesic of first choice (0.5−1 mg/kg in the presence of hemodynamic instability) is advisable, since ketamine produces less cardiovascular and respiratory depression when used with a neuromuscular blocker in a rapid induction sequence. For very unstable patients, intubation can be performed while maintaining spontaneous breathing with ketamine alone (without neuromuscular blockade).23 Atropine is only indicated if reflex bradycardia occurs in response to stimulation during laryngoscopy, which is more common in children. Cuffed tubes are currently the first choice at any age. Devices for difficult airway management, such as videolaryngoscopy, Frova-type introducers, and laryngeal masks, are available for all ages.24 In the "non-intubable, non-ventilatable" scenario, there are no percutaneous devices for children under 5 years of age; therefore, angiocatheters must be used in these cases. For patients between 5 and 10 years of age, such devices are available, but they have a narrow caliber that only allows oxygenation.25 Cervical control is preferably manual, as it is more comfortable, although the indications are increasingly restrictive (Appendix B Table 2 of the Supplementary material).
- B
Ventilation and oxygenation
The FiO2 required to achieve target saturations of 93–97% is administered to avoid hyperoxia. The smallest self-inflating bag (250 ml) should be excluded. It is essential to observe correct thoracic excursion and to auscultate good air entry. The tidal volume administered in invasive mechanical ventilation (IMV) should be 6−8 ml/kg of ideal body weight to achieve normal ventilation. Despite its variable correlation with arterial pCO2, capnography is useful. Among the possible NFRIs, tension or open pneumothorax, massive hemothorax, flail chest, and pulmonary contusion should be mentioned.26 Thoracic drainage is performed in the fourth or fifth intercostal space (mid- and anterior axillary line) or the second space on the midclavicular line. In cases of CRA, thoracotomy should be considered, especially for penetrating trauma, provided that experienced personnel are available.27,28
- C
Evaluation of circulation and bleeding
The hemodynamic situation is evaluated based on the heart rate, arterial pressure, perfusion, and other factors. The evaluation should include a diagnosis of the source of the hemorrhage. Although resuscitation will be discussed in depth later (in the "Hemorrhagic shock" section), it is important to note that venous access should be established within the first five minutes (the peripheral route in the antecubital fossa being the preferred choice). There are different types of shock: hypovolemic-hemorrhagic (the most common type, which will be discussed below), obstructive (pneumothorax or cardiac tamponade), distributive, and cardiogenic (due to thoracic contusion or electrocution). Traumatic shock is described as a dynamic combination of these mechanisms. For cardiac tamponade, the safest approach is the echo-assisted anterior intercostal approach.29 In CRA, reversible causes should be treated immediately, even before adrenaline is administered, and in parallel with compressions.28
- D
Neurological deficit
Neurological deficits are assessed using the Glasgow Coma Scale (GCS), which has been adapted for children under 2–3 years of age (Appendix B Table 3 of the Supplementary material). A motor GCS score of less than 4 implies loss of airway protection.27 Seizures in the early hours after traumatic brain injury (TBI) can occur without intracranial damage.30 They should be treated with benzodiazepines and, unless they persist, should not result in intubation. Pain and agitation should be treated aggressively, and non-pharmacological measures should be considered (e.g., presence of parents, toys, or videos). An NFRI is characterized by endocranial hypertension, pupillary abnormality, and bradycardia. The appearance of an erythematous rash on the upper part of the body is infrequent but characteristic.31 Hyperosmolar therapy with hypertonic saline (2−5 ml/kg at a concentration of 3% in 10−20 min) can be used for immediate treatment during crises. At present, the use of hypertonic saline is preferable to avoid the osmotic diuresis of mannitol. Hyperventilation is limited to a rescue maneuver until definitive measures are put in place.32
- E
Exposure and prevention of hypothermia
The patient should be exposed to proactively look for external injuries and then be quickly covered again. The temperature should be determined, and the patient should be actively warmed in case of hypothermia (temperature < 35 °C).33
Other considerationsUltrasound is included in the primary examination because it allows for the detection of some NFRIs (E-FAST).34 It must be performed without delaying the rest of the actions. A secondary evaluation begins once the patient is in a more stable condition. It includes a directed history and physical examination as well as complementary tests, such as blood and urine tests (including toxins) and imaging procedures (Appendix B Table 4 of the Supplementary material). Since children are more sensitive due to their developing tissues and have a longer life expectancy, radiation exposure for diagnostic purposes should be kept to a minimum. Liberal use of radiation exposure does not improve outcomes in stable patients and is associated with overdiagnosis and longer hospital stays. Restrictive but consensus-based protocols should be promoted.35
Hemorrhagic shockHemorrhagic shock is the leading cause of preventable mortality in pediatric trauma, surpassing the mortality rate observed in adults (36% versus 20–25%).36 Early identification and control are essential in this regard.
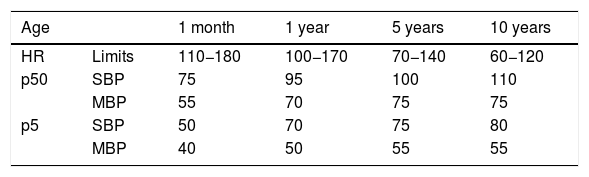
Pathophysiology of hemorrhagic shock in childrenThe increase in systemic vascular resistance maintains blood pressure up to blood loss volumes of 30–40%. Hypotension is a late sign ("decompensated shock").3 The first sign is tachycardia. Heart rate and blood pressure have wide normal ranges depending on age (Table 4).27 Slowing of capillary refill results in a mottled, cold appearance of the most distal parts of the body. “Pseudo-compromise“, a similar clinical situation caused by fear, pain, cold, or post-critical state,20 should be ruled out.
Heart rate and blood pressure. Ranges in pediatrics.
| Age | 1 month | 1 year | 5 years | 10 years | |
|---|---|---|---|---|---|
| HR | Limits | 110−180 | 100−170 | 70−140 | 60−120 |
| p50 | SBP | 75 | 95 | 100 | 110 |
| MBP | 55 | 70 | 75 | 75 | |
| p5 | SBP | 50 | 70 | 75 | 80 |
| MBP | 40 | 50 | 55 | 55 |
HR: heart rate; MAP: mean arterial blood pressure; SBP: systolic blood pressure. Approximation (1–10 years): SBP: p50 = 90 + age (years) × 2, p5 = 70 + age (years).
Damage control resuscitation is the strategy of choice, the salient elements of which are37:
- •
Recognize bleeding.
- •
Determine the need for a transfusion.
- •
Establish vascular access.
- •
Administer blood products.
- •
Avoid hemodilution, acidosis, hypocalcemia, and hypothermia.
- •
Rapid control of the source of the hemorrhage.
Establishing a vascular access in pediatric patients with vasoconstriction can be complicated. Peripheral access should be achieved within 5 min (60 s in CRA) or within two attempts in accessible areas and with the largest possible caliber. The most recommended locations are the antecubital fossa and saphenous route.38 Intraosseous access is the first alternative and may be the primary option if difficulty is anticipated. It is easy to place and can be performed in the proximal tibia (most frequently), with alternatives being the proximal humerus (in larger patients) and the distal femur.39
Volume and blood productsIdeally, no more than 20 ml/kg of crystalloids should be administered; excess administration is associated with a poorer course.40 Blood products should be prioritized, even in an out-of-hospital setting. The preferred ratio of red blood cell concentrates, plasma, and platelets is close to 1:1:1.41 The transfusion of group O whole blood with low titers of anti-A and anti-B IgG (LTOWB: Low-Titer Group O Whole Blood) has been proposed as a safe and fast alternative. However, further studies are needed to demonstrate its superiority.42
Vasoactive supportIf hypotension persists despite volume resuscitation, vasoactive support should be administered. Noradrenaline is the drug of choice despite scarce supporting evidence.43 In cases of cardiac dysfunction, adrenaline or dobutamine should be considered. These drugs can be administered conveniently diluted via the peripheral route.44
Clinical indicators and shock parametersThe goal of permissive hypotension in cases of uncontrolled bleeding is to administer the least amount of volume possible until the bleeding is controlled. If there is no central nervous system (CNS) involvement, a minimum blood pressure should be maintained at p5; if there is CNS involvement, it should reach at least p50. The chosen resuscitation target should be the minimum needed to ensure adequate tissue perfusion and oxygen supply.45 The Shock Index (heart rate divided by systolic blood pressure) is an early indicator that identifies patients at a higher risk for severe hemorrhaging and the need for intervention. In pediatrics, the Shock Index, Pediatric Age-Adjusted, is more appropriate. The reference values are: 1.22 for ages 4–6, 1 for ages 7–12, and 0.9 for ages 13–16 years.46 Less widespread and validated are the reverse shock index multiplied by the GCS and the ABC-D, which includes lactate and base excess (BE), though with promising results.47,48 Lactate, BE, and hemoglobin evolution over time are also useful.
Massive transfusion in pediatrics and goal-directed therapyThere is no consensus on the definition and activation criteria for massive transfusion. These criteria must be simple to ensure timely and rapid access to blood products.49 The most widely accepted criteria are:
- •
Transfusion of 40 ml/kg or 2 units of packed blood red cells (1–24 h).
- •
Rapid and uncontrolled blood loss.
- •
Estimated volume loss ≥ 40% of total blood volume or 40 ml/kg.50
Activation is often triggered by clinical manifestations of shock, a compatible injury mechanism, and significant bleeding. This is followed by targeted guidance and viscoelastic testing.45 It is advisable to determine prothrombin time, fibrinogen, and platelets. A prothrombin ratio > 1.5 is considered indicative of severe coagulopathy. Desirable levels are: hemoglobin between 7−9 g/dl and platelets > 50 × 109/l (> 100 × 109/l in the event of central nervous system bleeding). As mentioned in the "Volume and blood products" section, transfusions should be balanced with ratios close to 1:1:1. It is necessary to monitor ionic calcium levels and to supplement them if found to be low.33,41 In the event of severe bleeding, the empirical administration of tranexamic acid is recommended within the first three hours (15 mg/kg and infusion).51 Fibrinogen or cryoprecipitates are indicated in cases of hypofibrinogenemia (<150 mg/dl) or a compatible result in viscoelastic tests.33,45
Non-operative management strategy and damage control surgeryThe previously described measures are temporary until the bleeding is controlled. Non-operative management is the standard approach for patients with isolated solid organ injuries. However, patients with bleeding and instability despite volume resuscitation, or with rebleeding, require angioembolization or surgery. Embolization may reduce the need for surgery in pediatric patients with signs of persistent active bleeding.52 Finding contrast extravasation on a CT scan in a hemodynamically stable patient is not an indication for embolization.53 For patients who do not respond to the initial measures, even temporarily, damage control surgery should be considered. For complex cases, a multidisciplinary decision-making process is recommended, taking into account the lesions, the resuscitation specialist’s opinion, and the feasibility of transferring to a CT scan or intervention, as well as the need for emergent surgery.54,55
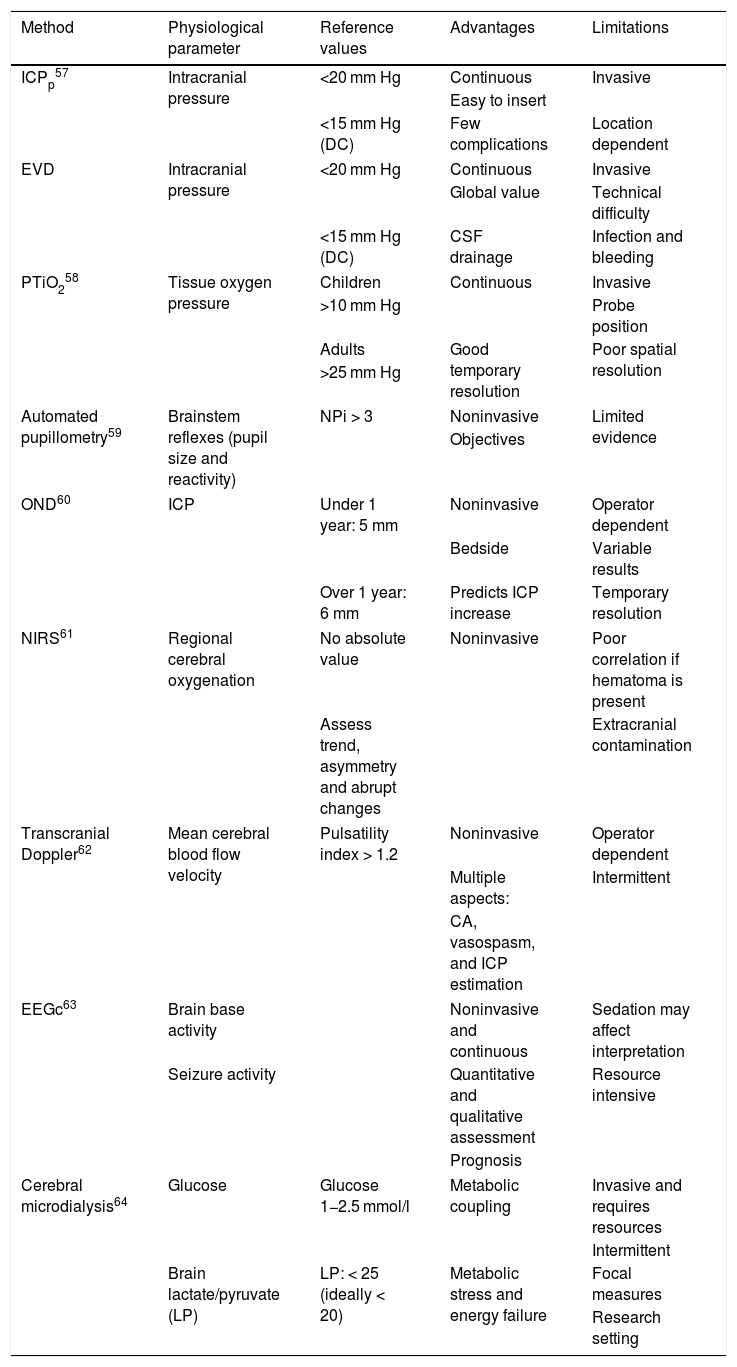
Care of head injuriesTBI remains one of the leading causes of mortality and morbidity in children, with an incidence of 134 per 100,000 person-years.56 The main aspects of care for children with TBI will be reviewed, with special emphasis on neuromonitoring (Table 5).
Neuromonitoring of the patient with traumatic brain injury.
| Method | Physiological parameter | Reference values | Advantages | Limitations |
|---|---|---|---|---|
| ICPp57 | Intracranial pressure | <20 mm Hg | Continuous | Invasive |
| Easy to insert | ||||
| <15 mm Hg (DC) | Few complications | Location dependent | ||
| EVD | Intracranial pressure | <20 mm Hg | Continuous | Invasive |
| Global value | Technical difficulty | |||
| <15 mm Hg (DC) | CSF drainage | Infection and bleeding | ||
| PTiO258 | Tissue oxygen pressure | Children | Continuous | Invasive |
| >10 mm Hg | Probe position | |||
| Adults | Good temporary resolution | Poor spatial resolution | ||
| >25 mm Hg | ||||
| Automated pupillometry59 | Brainstem reflexes (pupil size and reactivity) | NPi > 3 | Noninvasive | Limited evidence |
| Objectives | ||||
| OND60 | ICP | Under 1 year: 5 mm | Noninvasive | Operator dependent |
| Bedside | Variable results | |||
| Over 1 year: 6 mm | Predicts ICP increase | Temporary resolution | ||
| NIRS61 | Regional cerebral oxygenation | No absolute value | Noninvasive | Poor correlation if hematoma is present |
| Assess trend, asymmetry and abrupt changes | Extracranial contamination | |||
| Transcranial Doppler62 | Mean cerebral blood flow velocity | Pulsatility index > 1.2 | Noninvasive | Operator dependent |
| Multiple aspects: | Intermittent | |||
| CA, vasospasm, and ICP estimation | ||||
| EEGc63 | Brain base activity | Noninvasive and continuous | Sedation may affect interpretation | |
| Seizure activity | Quantitative and qualitative assessment | Resource intensive | ||
| Prognosis | ||||
| Cerebral microdialysis64 | Glucose | Glucose 1−2.5 mmol/l | Metabolic coupling | Invasive and requires resources |
| Intermittent | ||||
| Brain lactate/pyruvate (LP) | LP: < 25 (ideally < 20) | Metabolic stress and energy failure | Focal measures | |
| Research setting | ||||
CA: cerebral autoregulation; DC: decompressive craniectomy; OND: optic nerve sheath diameter; EVD: external ventricular drainage; EEGc: continuous electroencephalogram; NIRS: near-infrared spectroscopy; CSF: cerebrospinal fluid; ICPp: intraparenchymal intracranial pressure; CPP: cerebral perfusion pressure; PTiO2: tissue oxygen pressure.
Adapted from Agrawal et al.65.
The initial clinical examination is essential to classify and establish a prognosis. Thus, a motor GCS ≤ 3 is strongly predictive of a poor prognosis.66 Anisocoria is suggestive of increased intracranial pressure (ICP) and uncal herniation, requiring urgent treatment. Bilateral mydriasis is associated with high mortality. Automated pupillometry provides greater precision, and some of the derived indices may be of prognostic value.59
Intracranial pressureICP is the pressure exerted by the sum of the intracranial volumes (parenchymal tissue, blood, and cerebrospinal fluid). An increased intracranial volume that overcomes compensatory mechanisms (decreased compliance) can raise ICP, leading to cerebral compression, ischemia, herniation, and death. There are different methods available for measuring ICP; each method has different advantages and limitations (Table 5).67 ICP monitoring should be performed in patients with severe TBI (GCS ≤ 8) and injuries identified by brain CT (e.g., hematomas, contusions, swelling, herniation, or basal cistern compressions). Monitoring is also indicated in severe TBI without lesions, but with evidence in the examination of unilateral or bilateral decorticate posturing or arterial hypotension. Finally, ICP monitoring is also indicated in severe polytrauma and TBI when correct neurological monitoring is impossible due to other reasons, such as lung injury or hemodynamic instability. For patients without clear indications (e.g., moderate TBI with risk injuries), or in the early stages of care, noninvasive techniques (e.g., optic nerve sheath diameter or Doppler ultrasound) may be useful for follow-up and making decisions about invasive monitoring. In patients undergoing invasive monitoring, these techniques remain relevant, as they provide supplementary information.68
Cerebral perfusion pressureICP monitoring allows the calculation of cerebral perfusion pressure (CPP): CPP = mean arterial pressure (MAP)-ICP. Clinicians can act on CPP by lowering ICP, increasing MAP, or both. It is important to adjust the CPP target according to patient age: under 2 years > 45 mm Hg, between 2–8 years > 60 mm Hg, and over 8 years > 70 mm Hg.69
Multimodal neuromonitoringCerebral flow and autoregulationThere is a consensus that complementary parameters, such as autoregulation, oxygenation, and cerebral metabolism, should be incorporated alongside ICP. Loss of cerebral autoregulation (CA) is common after TBI, which makes the brain more vulnerable. Management guided by fixed CPP targets is insufficient. For example, loss of CA increases the risk of cerebral edema. Conversely, patients with preserved CA may benefit from higher CPP, which decreases ICP.70 CA assessment is based primarily on the reactivity index (PRx). This is a moving correlation coefficient between spontaneous slow wave changes between MAP and ICP during a 5-min window. PRx can take values from −1 to +1. Negative values represent an inverse relationship and intact CA, indicating a better clinical outcome, whereas positive values indicate altered CA.71 By constructing the CPP-PRx curve, one can calculate the optimal CPP, which is the area of the curve that makes PRx more negative. This curve also allows for the treatment of endocranial hypertension by increasing CPP, provided that CA is preserved (PRx < 0). Though evidence is limited in children, pending trials, there are promising results in adults.65 Transcranial Doppler ultrasound measures cerebral blood flow velocity and is used to calculate the pulsatility index to estimate ICP and CPP. In pediatrics, a good correlation has been described in the determination of CPP, although the evidence on the usefulness of the formulas for estimating ICP is not conclusive.62
Oxygenation and metabolismCerebral oximetry with near-infrared spectroscopy provides information on global oxygenation in all the vascular compartments. While the absolute value has not been shown to be useful, changes over time may help in monitoring cerebral perfusion.61 Cerebral tissue oxygenation (PTiO2) and cerebral microdialysis provide information on perfusion and cellular metabolism. PTiO2 helps prevent tissue hypoxia and adjust therapies to lower ICP. In pediatrics, values < 10−20 mm Hg are associated with ischemia and a poorer prognosis.58 Microdialysis allows for the analysis of brain metabolites such as glucose and lactate/pyruvate, which serve as indicators of ischemia or mitochondrial dysfunction.72
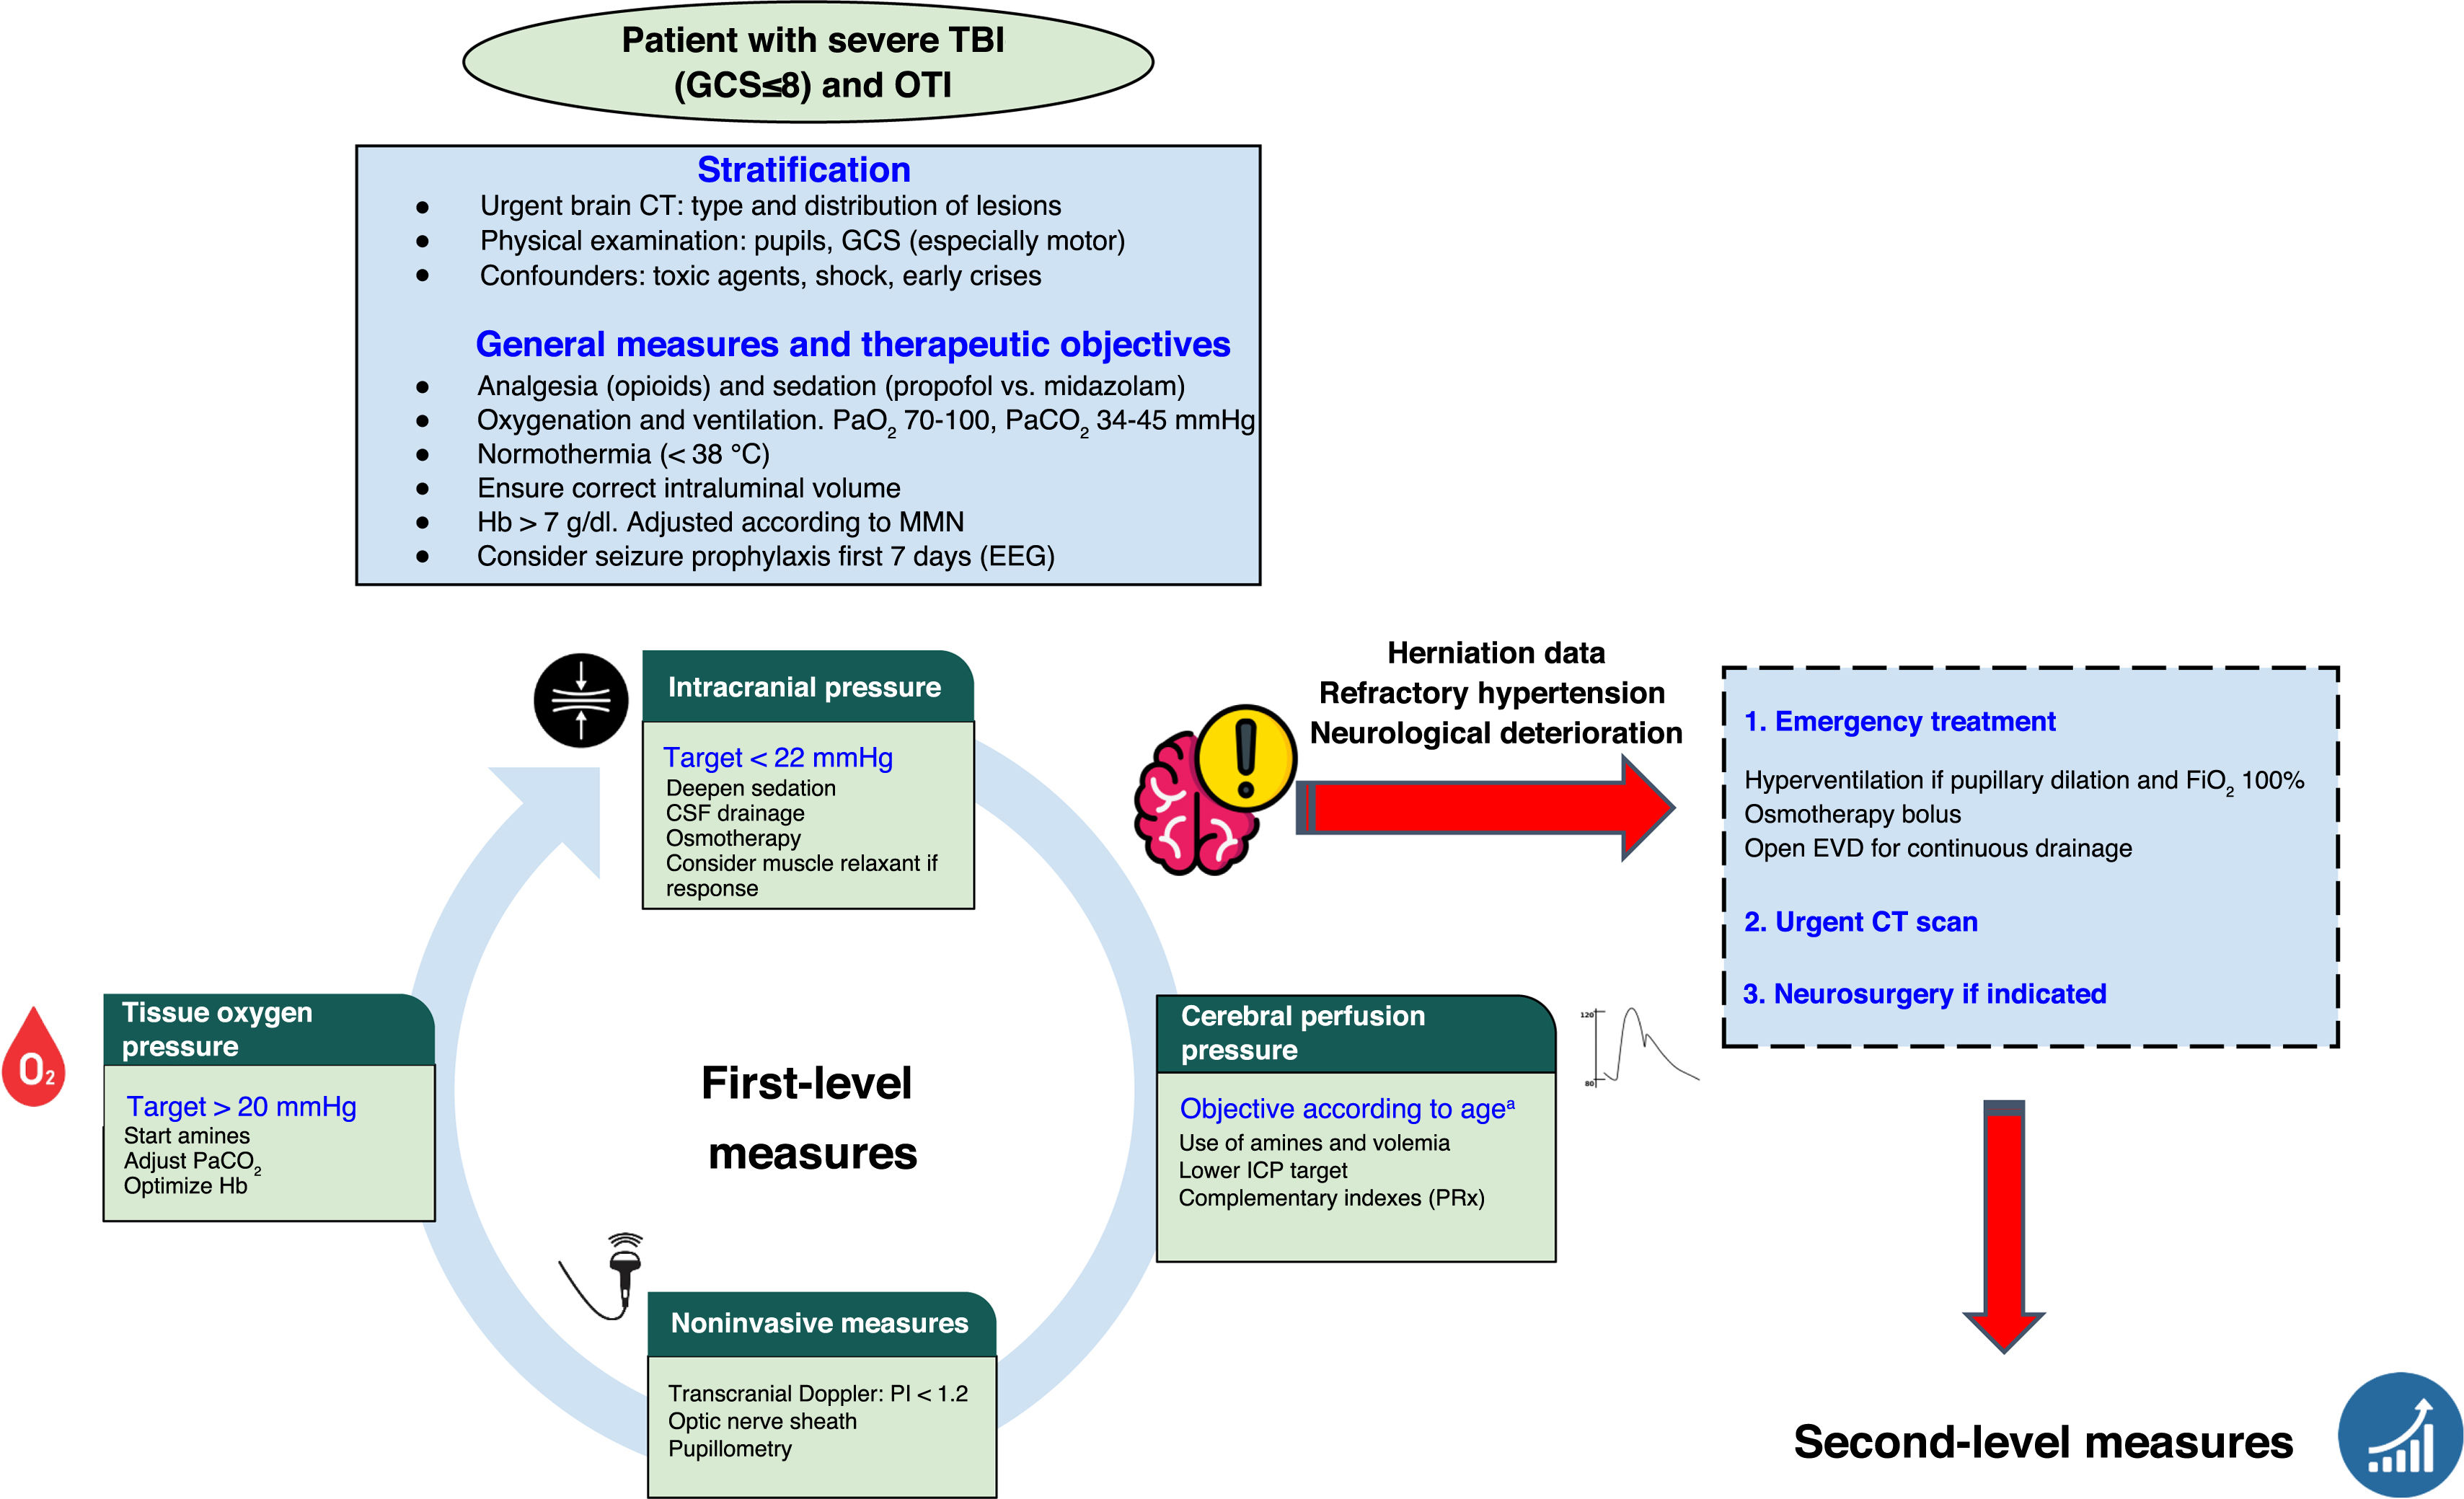
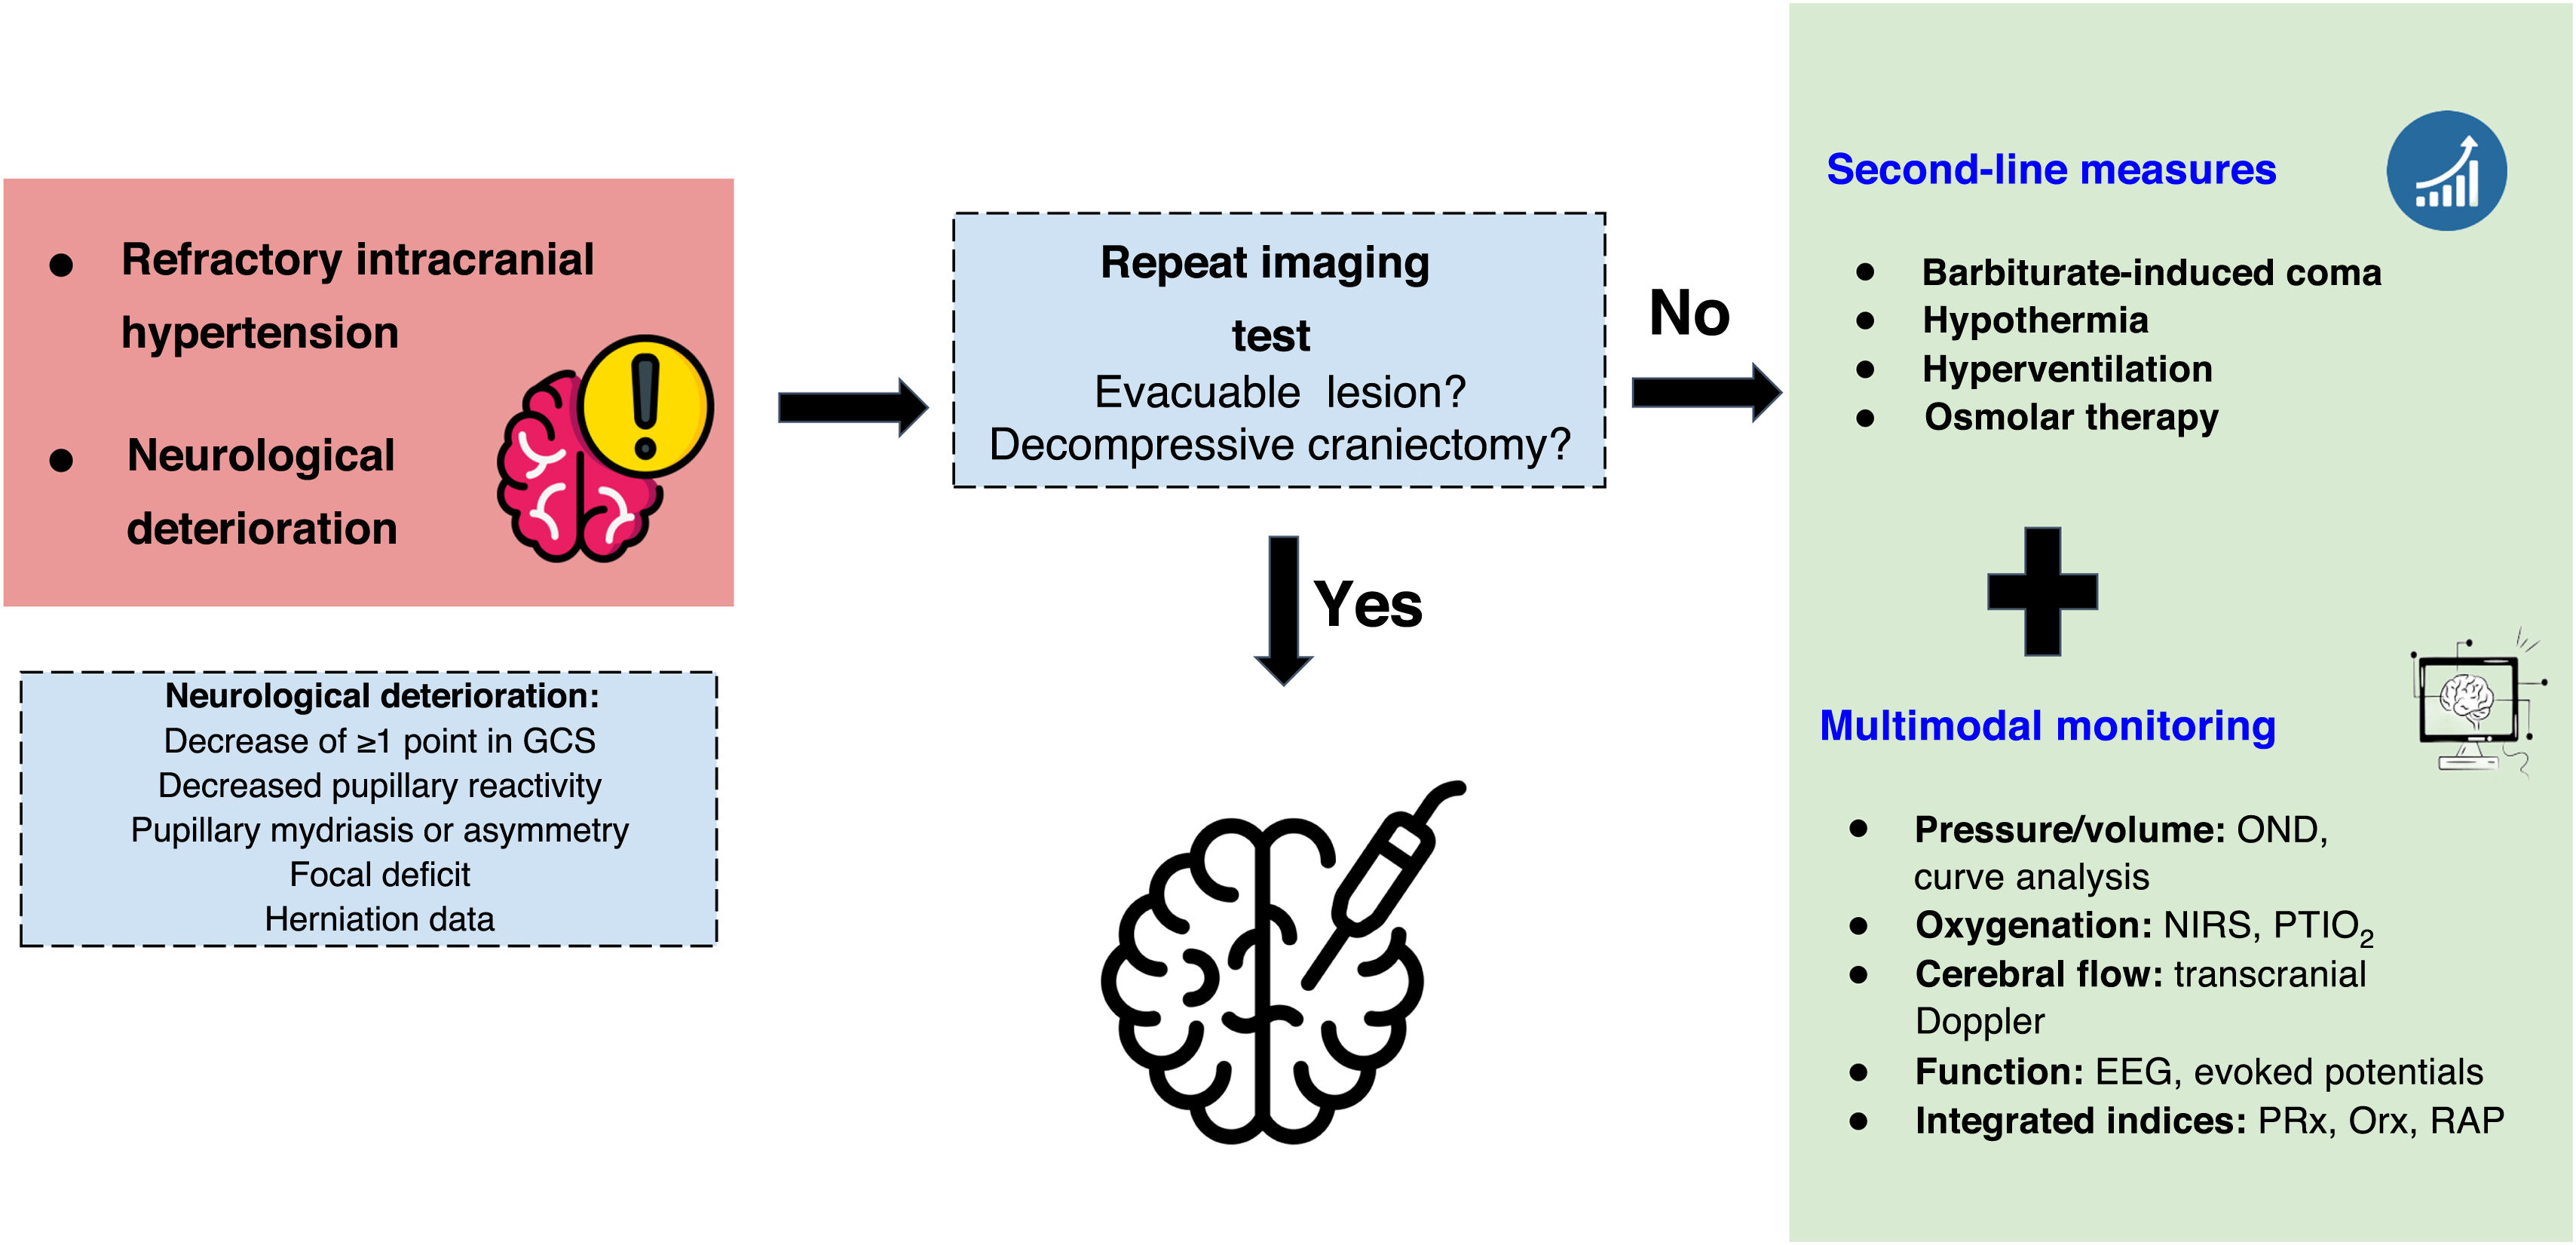
General management according to current evidence (Pediatric TBrain trauma Foundation guidelines)Figs. 1 and 2 propose treatment schemes in accordance with the Brain trauma Foundation’s algorithms for managing severe pediatric TBI.73Fig. 1 includes the basic measures, such as securing the airway, sedation, and maintaining homeostasis. A cranial CT scan is essential to rule out lesions requiring urgent surgery. If not, then ICP monitoring is indicated. Cerebral herniation may occur at any time, during initial resuscitation or in the context of refractory intracranial hypertension. Treatment is emergent, regardless of the ICP value. Treatment includes hyperventilation, osmotherapy (with hypertonic saline preferred, due to the lower risk of osmotic diuresis), increased MAP, or opening of the external intraventricular drainage. Apart from targeting an ICP < 20 mm Hg and < 15 mm Hg in decompressive craniectomies, it is important to have a CPP > 40 mm Hg in young children and > 50 mm Hg in adolescents, using PRx as a help to obtain the ideal value. If, despite the first-level measures, the patient persists with intracranial hypertension, a decompressive craniectomy may be considered (Fig. 2). Medical interventions may include barbiturate-induced coma, moderate hypothermia, and hyperventilation with CO2 levels of 28−34 mm Hg while monitoring for ischemia (cerebral oxygenation monitoring). In summary, all the information must be considered, and guidelines must be implemented according to the patient's context and response.

First-line treatment algorithm for severe traumatic brain injury in pediatrics.
EVD: external ventricular drainage; EEG: electroencephalogram; GCS: Glasgow Coma Score; Hb: hemoglobin; OTI: orotracheal intubation; PI: pulsatility index; CSF: cerebrospinal fluid; MMN: multimodal neuromonitoring; PaCO2: arterial carbon dioxide pressure; PaO2: arterial oxygen pressure; ICP: intracranial pressure; PRx: pressure reactivity index; TBI: traumatic brain injury.
a Target cerebral perfusion pressure according to age: under 2 years > 45 mm Hg, between 2–8 years > 60 mm Hg, and over 8 years > 70 mm Hg.

Second-line treatment algorithm for severe traumatic brain injury in pediatrics.
OND: optic nerve diameter; EEG: electroencephalogram; GCS: Glasgow Coma Scale; NIRS: near-infrared spectroscopy; ORx: oxygen reactivity index; PRx: pressure reactivity index; PtiO2: tissue oxygen pressure; RAP: cerebrovascular compensatory reserve.
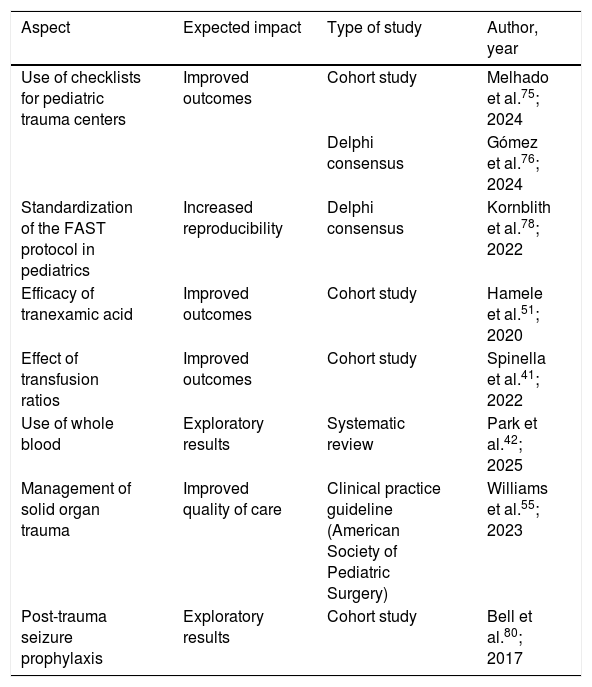
There have been relevant advances in the management of pediatric trauma in recent years (Table 6), though substantial knowledge gaps remain. Some recent proposals and priority lines of development are summarized below.
Recent evidence in pediatric trauma.
| Aspect | Expected impact | Type of study | Author, year |
|---|---|---|---|
| Use of checklists for pediatric trauma centers | Improved outcomes | Cohort study | Melhado et al.75; 2024 |
| Delphi consensus | Gómez et al.76; 2024 | ||
| Standardization of the FAST protocol in pediatrics | Increased reproducibility | Delphi consensus | Kornblith et al.78; 2022 |
| Efficacy of tranexamic acid | Improved outcomes | Cohort study | Hamele et al.51; 2020 |
| Effect of transfusion ratios | Improved outcomes | Cohort study | Spinella et al.41; 2022 |
| Use of whole blood | Exploratory results | Systematic review | Park et al.42; 2025 |
| Management of solid organ trauma | Improved quality of care | Clinical practice guideline (American Society of Pediatric Surgery) | Williams et al.55; 2023 |
| Post-trauma seizure prophylaxis | Exploratory results | Cohort study | Bell et al.80; 2017 |
In the prehospital and triage setting, recent publications have proposed a version of the Pediatric Trauma Injury Severity Score.12 Models adapted to low-resource settings, such as the Pediatric Resuscitation and Trauma Outcome, could also be useful.74 It is noteworthy that some centers use checklists that include the availability of personnel, equipment, and protocols. This practice has been associated with lower mortality in the first year, provided there is high compliance.75 Similarly, a Spanish group proposes using checklists during initial management to improve the quality of care.76
One possible organizational improvement is the development of trauma systems (TS) in our setting. Currently, Spain lacks a coordinated strategy to promote the development of TS for both the pediatric and adult populations. Some regions (Autonomous Communities) have made progress in creating "trauma codes", which include criteria for hospital referral and categorization. However, these experiences are heterogeneous and of limited application. The health agencies must promote the implementation of an integrated plan in all territories that includes training, research, and registries.77
Regarding initial care and resuscitation, ultrasound has been progressively incorporated. However, its usefulness in pediatrics is limited. Recent consensuses have been proposed to improve standardization and facilitate incorporation of the technique.78 There has also been an increase in the use of endovascular techniques. Despite positive results, these techniques are not widely used, so integrating them into local protocols is recommended. In the management of shock, the use of blood products and blood components stands out (Table 6). It should be noted that most of the evidence is observational or has been extrapolated from adults, thus highlighting the need for more specific research.37 To this end, multidisciplinary registries may be useful in improving clinical care and promoting research.79
Regarding TBI, mention should be made of the development of the Approaches and Decisions for Acute Pediatric TBI Cohort, which includes 1000 patients with head injuries, and has produced several recent publications that have contributed to the current state of the evidence80 (Table 6).
ConclusionsTrauma is the leading cause of mortality in children, requiring care adapted to their unique needs. Implementing integrated trauma systems with code deployment is essential for improving outcomes. Resuscitation strategies should focus on early shock identification and the rational use of blood products, though evidence is still emerging. In TBI, advanced neuromonitoring allows for more precise management and associated prognostic improvements. Further research is needed in pediatric trauma and the development of registries.
Declaration of Generative AI and AI-assisted technologies in the writing processSuch use has been made to correct typographical and spelling errors, not for the generation of content.
All authors have contributed to this manuscript and have given their approval.
Financial supportThis project has received no financial support.
None of relevance.
The following is Supplementary data to this article:




